Cranial Nerves for FMGE: The Twelve-Nerve System, Not Twelve Separate Facts
By Dr. Utsav Bhattacherjee, MBBS, MBA · 17 September 2026 · 10 min read
Cranial nerve questions are built to test one thing above all: can you connect a specific deficit to the exact nerve responsible, fast. Twelve nerves, each with a defined function, is genuinely learnable as a system rather than twelve separate facts — the number, the type, and the test all follow a logical structure once you see it.
The Numbering and the Type
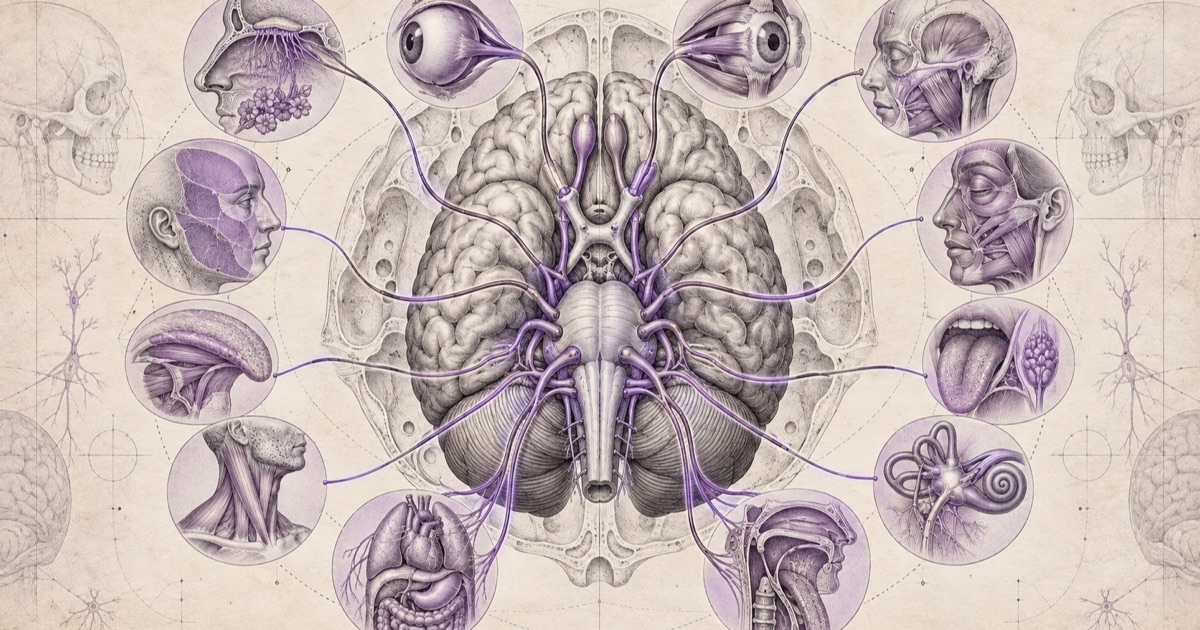
Cranial nerves are numbered I through XII in the order they exit the brainstem, and each is classified as sensory, motor, or mixed (both). The classic mnemonic for the order (Oh Oh Oh To Touch And Feel Very Good Velvet Ah Heaven) pairs with a second mnemonic for type (Some Say Marry Money But My Brother Says Big Brains Matter More) — running both together tells you the name and whether it carries sensory fibres, motor fibres, or both, for all twelve in one pass.
The Twelve, With Function
| Nerve | Name | Type | Key Function |
|---|---|---|---|
| I | Olfactory | Sensory | Smell |
| II | Optic | Sensory | Vision |
| III | Oculomotor | Motor | Most eye movements, pupil constriction, eyelid opening |
| IV | Trochlear | Motor | Downward eye movement when adducted |
| V | Trigeminal | Mixed | Facial sensation, chewing muscles |
| VI | Abducens | Motor | Eye abduction |
| VII | Facial | Mixed | Facial expression, taste (anterior two-thirds of tongue) |
| VIII | Vestibulocochlear | Sensory | Hearing, balance |
| IX | Glossopharyngeal | Mixed | Gag reflex (sensory limb), taste (posterior tongue) |
| X | Vagus | Mixed | Gag reflex (motor limb), parasympathetic to viscera |
| XI | Accessory | Motor | Sternocleidomastoid, trapezius |
| XII | Hypoglossal | Motor | Tongue movement |
CN I and II: The Two Purely Sensory Nerves Tested First
CN I (olfactory) and CN II (optic) are the two purely sensory nerves tested first, and both are frequently skipped in routine bedside exams despite being genuinely testable and genuinely high-yield. CN I is tested with a distinct, non-noxious smell (coffee, not ammonia, which would trigger CN V pain fibres instead of true olfaction) presented to each nostril separately. CN II is tested through visual acuity, visual fields, and the pupillary light reflex, and it’s worth remembering that CN II carries the afferent limb of the pupillary light reflex while CN III carries the efferent limb — a fixed, dilated pupil with normal vision otherwise points toward a CN III problem, while a genuinely blind eye with no light perception points toward CN II.
A lesion at the optic chiasm specifically produces bitemporal hemianopia — loss of the outer (temporal) visual field in both eyes — because the chiasm is exactly where fibres from the nasal half of each retina cross to the opposite side. A pituitary tumour compressing the chiasm from below is the classic cause, and bitemporal hemianopia in a vignette is essentially always pointing toward chiasm-level compression rather than a lesion anywhere else along the visual pathway.
What Testing Each Nerve Actually Looks Like
CN III, IV, and VI control eye movement together, which is why a single finding — diplopia, or an eye that won’t move in a specific direction — needs all three considered as a group rather than in isolation. A down-and-out eye position with ptosis points to CN III; an eye that can’t look down when adducted points to CN IV (trochlear); an eye that can’t abduct points to CN VI.
CN V (trigeminal) is tested through the corneal reflex — touching the cornea should produce a blink, and the afferent limb of that reflex is CN V while the efferent limb (the actual blink) is CN VII. A vignette describing an absent corneal reflex with normal facial movement elsewhere is isolating the sensory afferent limb specifically, not a facial nerve problem.
CN VII (facial) lesions are classically split by location: an upper motor neuron lesion spares the forehead (since forehead muscles receive bilateral cortical input), while a lower motor neuron lesion — Bell’s palsy being the classic example — affects the entire half of the face including the forehead. This single distinction, forehead sparing versus forehead involvement, is one of the most reliably tested facts in the entire cranial nerve topic.
CN VIII (vestibulocochlear) carries both hearing and balance information, and it’s tested through the Weber and Rinne tests for hearing, alongside balance and nystagmus assessment for the vestibular component. A unilateral sensorineural hearing loss with associated balance problems and tinnitus is the classic combination pointing toward CN VIII pathology, such as a vestibular schwannoma, rather than an outer or middle ear problem affecting hearing alone.
CN IX and X are tested together through the gag reflex: IX carries the afferent (sensory) limb, X carries the efferent (motor) limb that actually elevates the palate. A vignette describing asymmetric palate elevation on gagging, with the uvula deviating away from the affected side, is describing a CN X lesion on the side the uvula moves away from.
CN XI (accessory) controls the sternocleidomastoid and trapezius, tested by asking the patient to turn their head against resistance and shrug their shoulders. CN XII (hypoglossal) controls tongue movement, and a lesion causes the tongue to deviate toward the side of the lesion on protrusion — the tongue points toward the weak side, not away from it, which is the detail worth locking in rather than assuming the deviation direction intuitively.
Where Each Nerve Actually Originates
Grouping the twelve nerves by their brainstem level of origin is a second organisational layer worth having alongside the numbered list, since some exam questions describe a lesion location rather than naming the nerve directly. CN I and II don’t originate from the brainstem at all — they’re extensions of the forebrain itself. CN III and IV originate from the midbrain. CN V, VI, VII, and VIII originate from the pons. CN IX, X, XI, and XII originate from the medulla.
This grouping explains a genuinely testable pattern: a single brainstem stroke or lesion at one level tends to produce a cluster of cranial nerve deficits from that same level together, rather than an isolated single-nerve deficit. A lesion producing both facial weakness (VII) and hearing loss (VIII) together, for instance, is consistent with a single pontine lesion affecting both nerves at their shared level of origin, rather than two coincidentally separate problems.
CN VIII specifically also sits close enough to CN VII within the internal auditory canal that a vestibular schwannoma growing there frequently compresses both nerves as it enlarges, which is exactly why facial weakness developing alongside progressive hearing loss and tinnitus is a classic combination pointing toward that specific tumour rather than a more general brainstem process.
How Cranial Nerves Are Tested on FMGE
Cranial nerve questions arrive in three recognisable shapes, and identifying which one you are looking at shortens the work considerably. The first names a lost function and asks which nerve carries it — pure recall, and the table above answers it. The second describes a reflex with only one limb missing, which is the sensory-motor pairing structure described below. The third gives a lesion SITE rather than a symptom, and expects you to know which nerves pass through it. That third shape is the one most candidates have not prepared for specifically, and it is the most reliably scored once you have.
Two sites account for most of those site-based questions. The cavernous sinus transmits CN III, IV, V1, V2 and VI, so a lesion there produces ophthalmoplegia affecting several eye movements at once TOGETHER with sensory loss over the forehead and cheek — the combination of eye-movement failure and facial sensory loss on the same side is the giveaway, because no single nerve lesion produces both. The jugular foramen transmits CN IX, X and XI, so a lesion there pairs swallowing and voice problems with weakness of the sternocleidomastoid and trapezius, a grouping that makes no sense unless you know the three nerves leave together.
The practical consequence is that grouped deficits should send you looking for a shared exit point rather than for one nerve that could explain everything. A single nerve rarely explains a multi-nerve picture, and the exam uses that fact deliberately. Working through FMGE previous year questions is where this pattern becomes visible — the same handful of localisation sites recur across sessions. For the wider subject, how to prepare Anatomy for FMGE sets out where cranial nerves sit against the rest of the syllabus, and the FMGE Anatomy subject page collects the topic-level material alongside it.
The Pattern Worth Noticing
Several of these nerves are tested in pairs specifically because one carries the sensory half of a reflex and another carries the motor half — corneal reflex (V sensory, VII motor) and gag reflex (IX sensory, X motor) are the two clearest examples. Recognising this sensory-motor pairing structure means a deficit in only one half of a reflex arc points cleanly to one specific nerve, rather than requiring twelve nerves to be considered independently every time.
Reading a cranial nerve vignette efficiently means checking, in this order: which specific function is described as lost, which nerve or nerve pair that function traces back to, and — if a lesion location is given instead of a symptom — which brainstem level that location corresponds to and which nerves originate there.




